SELECT asked a question that a weight-loss measurement cannot answer: could weekly injected semaglutide reduce serious cardiovascular events in people who already had cardiovascular disease but did not have diabetes? Across 17,604 randomized participants, the trial found fewer first events in a combined outcome of cardiovascular death, nonfatal heart attack, or nonfatal stroke. That is evidence about clinical events, not simply a change on the scale.
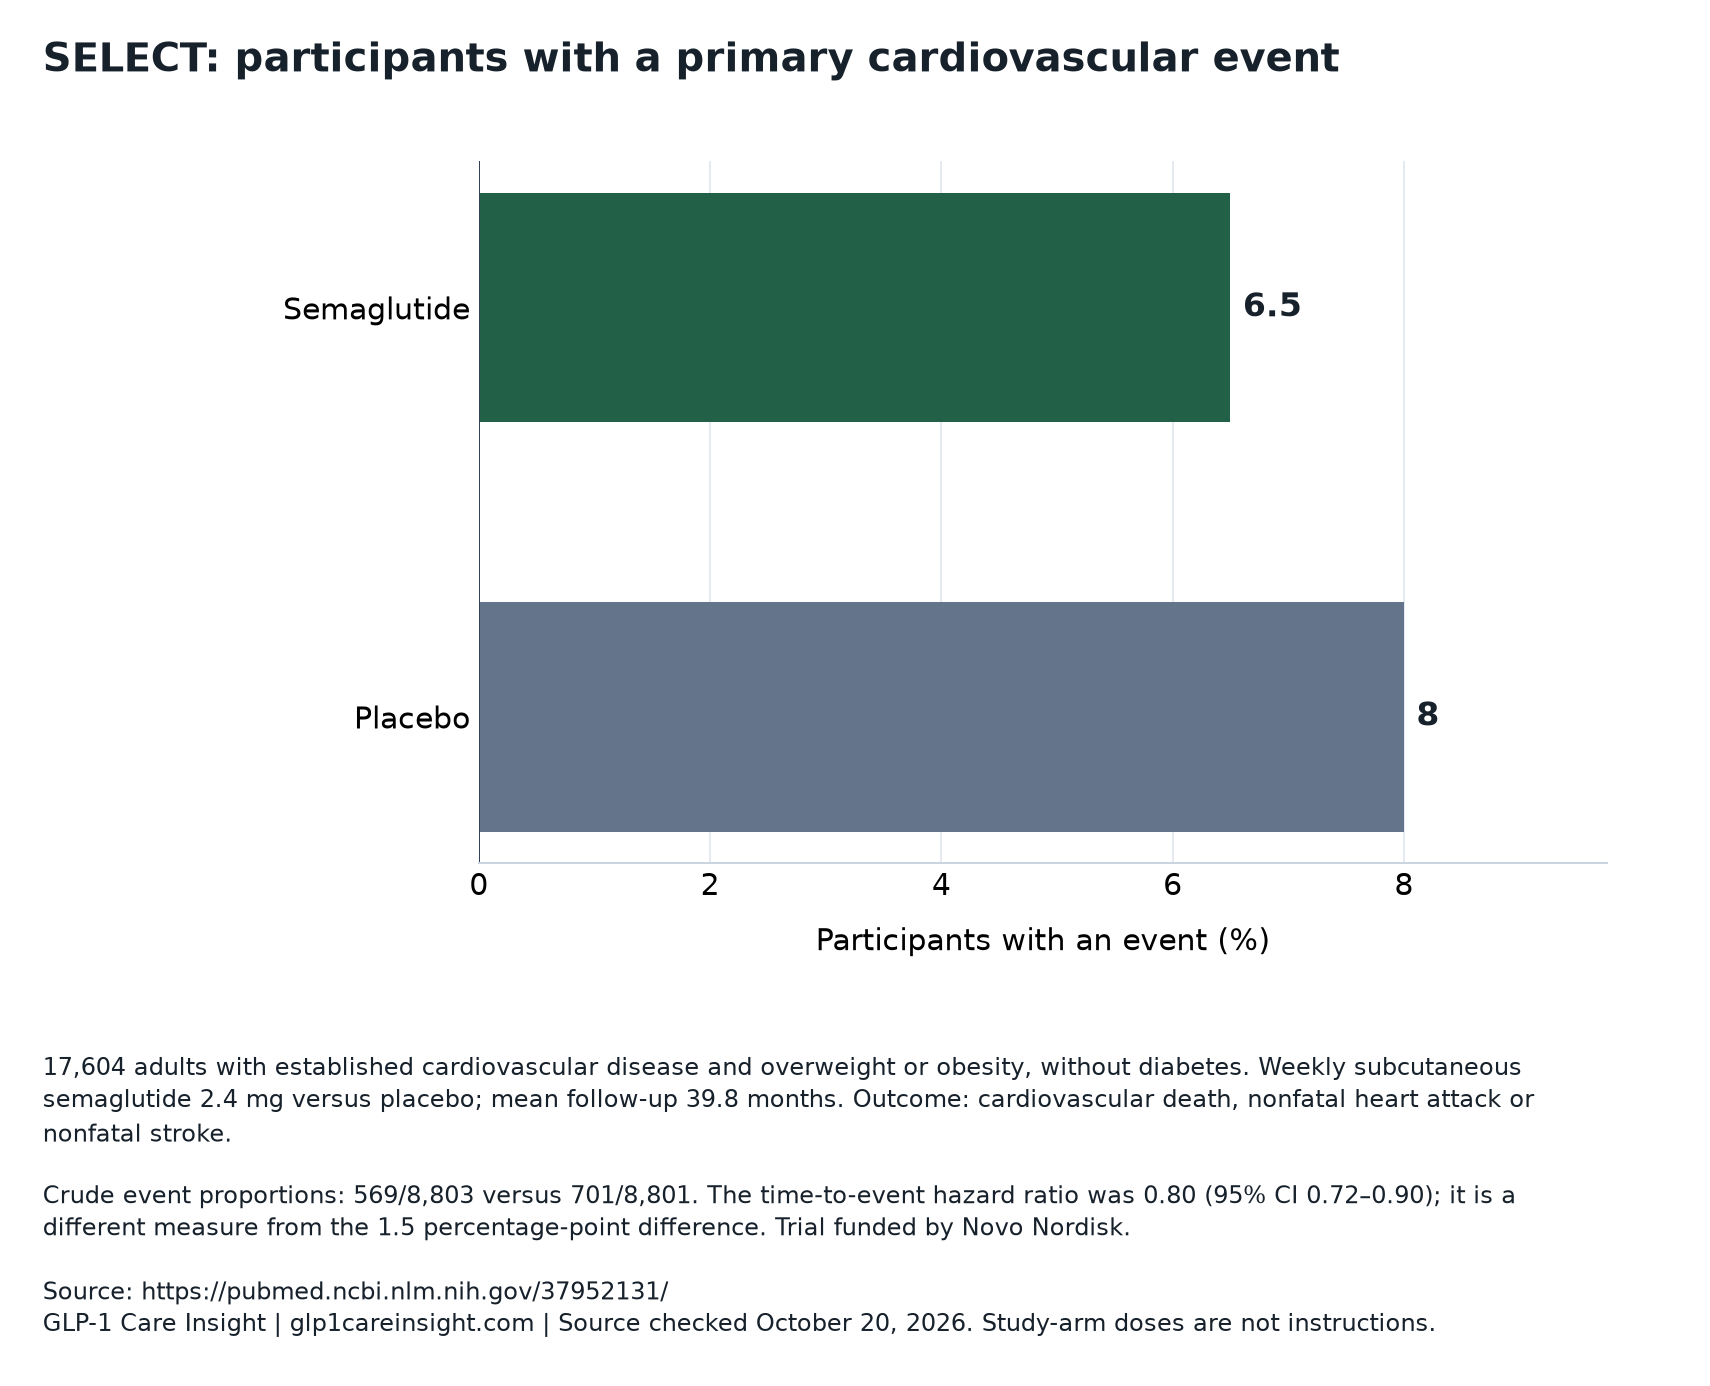
The headline result—a 20% lower hazard—needs its companion numbers. Primary events occurred in 6.5% of the semaglutide group and 8.0% of the placebo group over a mean follow-up of 39.8 months. Adverse events also caused more permanent treatment discontinuations with semaglutide. This analysis uses the indexed primary-report abstracts and available official FDA material; it does not represent a review of all full texts, protocols, or supplements.
At a glance
- Who was studied
- 17,604 adults aged 45 or older with preexisting cardiovascular disease, BMI of at least 27, and no history of diabetes.Sources: [1]
- What was compared
- Once-weekly subcutaneous semaglutide, with a study dose of 2.4 mg, versus placebo; both groups received standard cardiovascular care and lifestyle counseling.
- Primary cardiovascular result
- 569 of 8,803 participants versus 701 of 8,801 had a first primary event: 6.5% versus 8.0%; hazard ratio 0.80, 95% confidence interval 0.72–0.90.Sources: [1]
- Observation time
- Mean follow-up was 39.8 months; mean exposure to assigned semaglutide or placebo was 34.2 months.Sources: [1]
- Adverse-event discontinuation
- Adverse events led to permanent discontinuation of trial treatment in 16.6% of the semaglutide group and 8.2% of the placebo group.Sources: [1]
SELECT tested prevention after cardiovascular disease was established
Eligibility is central to interpreting SELECT. Participants were at least 45 years old, had a body mass index of 27 or higher, had preexisting cardiovascular disease, and had no history of diabetes. BMI relates weight to height; it was an entry criterion here, not the outcome used to establish cardiovascular benefit. The trial therefore addressed a specific intersection of cardiovascular disease and elevated body weight.
This is a secondary-prevention population: people already had cardiovascular disease before treatment assignment. Primary prevention asks whether treatment prevents a first cardiovascular disease event in people without established disease. SELECT does not answer that different question, and its event percentages should not be presented as the expected experience of everyone seeking weight treatment.
Baseline risk matters because an intervention’s absolute benefit depends partly on how often the outcome would otherwise occur. The placebo group’s 8.0% observed event proportion describes risk within this trial’s population, care setting, and observation period. It is not a universal untreated risk estimate, nor a personalized forecast for someone with a different medical history.
Randomization separated the treatment comparison from ordinary care
SELECT was a multicenter, double-blind, randomized, placebo-controlled superiority trial. Random assignment allocated 8,803 participants to semaglutide and 8,801 to placebo. Double blinding was intended to keep treatment assignment concealed from participants and investigators. A superiority design asks whether the intervention performs better than its comparator, rather than merely showing that the two are sufficiently similar.
The study intervention was subcutaneous semaglutide—an injection under the skin—given once weekly at a study dose of 2.4 mg. That dose identifies the trial arm; it is not an instruction for starting or adjusting treatment. Semaglutide is a glucagon-like peptide-1 receptor agonist, commonly shortened to GLP-1 receptor agonist.
Importantly, placebo did not mean no cardiovascular treatment. FDA’s official account states that both groups received standard cardiovascular care and lifestyle counseling. The comparison therefore concerns adding the assigned intervention in that setting, not replacing established care. Novo Nordisk funded SELECT. Funding is relevant context, while the randomized design and reported results remain the basis for evaluating the finding.
STUDY DATA · GLP-1 Care Insight
SELECT: participants with a primary cardiovascular event
17,604 adults with established cardiovascular disease and overweight or obesity, without diabetes. Weekly subcutaneous semaglutide 2.4 mg versus placebo; mean follow-up 39.8 months. Outcome: cardiovascular death, nonfatal heart attack or nonfatal stroke.
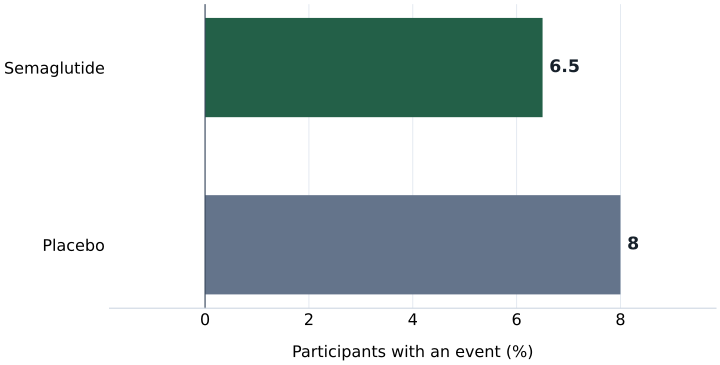
| Study group | Participants with an event (%) |
|---|---|
| Semaglutide | 6.5 |
| Placebo | 8 |
Crude event proportions: 569/8,803 versus 701/8,801. The time-to-event hazard ratio was 0.80 (95% CI 0.72–0.90); it is a different measure from the 1.5 percentage-point difference. Trial funded by Novo Nordisk.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
The primary outcome combined three serious events
The primary endpoint was the first occurrence of cardiovascular death, nonfatal myocardial infarction, or nonfatal stroke. Myocardial infarction means heart attack. Combining these outcomes lets a trial test whether treatment changes the occurrence of a clinically important group of events. It does not make the three components identical in severity, frequency, or response to treatment.
The analysis was time-to-first-event. It considered when a participant first experienced one of the qualifying outcomes, rather than simply counting every subsequent event. Someone who had a nonfatal heart attack and later another qualifying event would not contribute two separate first events to this primary analysis. The endpoint consequently does not describe the total burden of recurrent events.
A lower composite hazard does not establish that each component improved individually. The indexed SELECT abstract reports the combined primary result but does not supply the component-specific estimates needed for that assessment. A useful question when reading a cardiovascular claim is therefore: does the evidence concern the combined outcome, a particular component, or both?
| Component | What qualifies | Interpretive boundary |
|---|---|---|
| Cardiovascular death | Death attributed to cardiovascular causes | The composite result alone does not quantify a separate mortality benefit. |
| Nonfatal myocardial infarction | A heart attack that was not fatal | The abstract does not provide its individual treatment estimate. |
| Nonfatal stroke | A stroke that was not fatal | A lower composite hazard does not prove an equal reduction in stroke. |
The 20% figure and the 1.5-point difference measure different things
There were 569 participants with a primary event in the semaglutide group and 701 in the placebo group. The reported proportions were 6.5% and 8.0%. Subtracting those rounded percentages gives a crude absolute difference of 1.5 percentage points: approximately 15 fewer participants with a first event per 1,000 assigned participants over the observed trial period. That is a group-level description, not a promise about any individual.
The hazard ratio was 0.80. A hazard compares the rate at which first events occur among participants still at risk over follow-up. Subtracting 0.80 from 1 gives the reported 20% relative hazard reduction. It is not a 20-percentage-point reduction, and it does not mean that 20 of every 100 participants avoided an event.
The crude proportions do not reproduce the hazard ratio exactly because they omit event timing and differences in available observation time. Dividing the rounded 6.5% by 8.0% answers a different question from the time-to-event model. Keeping both measures visible is more informative than choosing whichever sounds larger; the evidence-questions guide offers a framework for examining numerical claims.
Confidence intervals describe precision, not a personal benefit range
SELECT’s hazard ratio had a 95% confidence interval of 0.72 to 0.90. On the relative-hazard scale, those limits correspond to reductions of 28% and 10%. The interval excludes 1.0, the value representing no difference in hazard. It supports a cardiovascular benefit in the studied population while showing that the estimated magnitude is not known with unlimited precision.
A confidence interval is not a statement that an individual’s benefit will fall between those limits. It summarizes statistical uncertainty around the trial’s estimated comparison under the analysis assumptions. It also does not capture every other uncertainty, such as how well results apply to a different population, formulation, or care environment.
SELECT was event-driven, meaning its design centered on accumulating outcome events rather than merely measuring weight at a single visit. Its large enrollment and 1,270 participants with a first primary event provide substantial outcome information. Even so, the primary result cannot by itself identify who benefits most, establish every component effect, or explain the biological pathway responsible.
Almost 40 months of follow-up is not 40 months of exposure for everyone
Mean follow-up was 39.8 months, with a standard deviation of 9.4 months. Mean exposure to semaglutide or placebo was shorter: 34.2 months, with a standard deviation of 13.7 months. Follow-up means observation for outcomes; exposure means time receiving the assigned trial product. These describe related but different aspects of the study.
The averages should not be read as a fixed treatment duration completed by every participant. The standard deviations indicate variation around those means. Nor should the difference between average follow-up and exposure be treated as a planned medication-free interval. The abstract does not provide enough detail to reconstruct each participant’s treatment and observation history.
The trial supports a conclusion over the period actually observed, not a lifetime estimate or a constant annual benefit. Dividing the absolute event difference by roughly three years would impose an untested assumption about how benefit accumulates. Similarly, SELECT does not establish how long protection persists after treatment ends or what happens under a particular interruption schedule.
Discontinuation is a substantial part of the result
Adverse events led to permanent trial-product discontinuation in 1,461 semaglutide participants and 718 placebo participants: 16.6% versus 8.2%. The difference is 8.4 percentage points. These were discontinuations attributed to adverse events, not the total frequency of all symptoms, all serious adverse events, or every possible reason for stopping treatment.
This finding prevents a blanket description of the intervention as simply safe or easy to tolerate. It also cannot be placed against the 1.5-percentage-point cardiovascular difference as though the two outcomes were interchangeable. Stopping medication because of an adverse event and experiencing a heart attack, stroke, or cardiovascular death have different meanings and consequences.
The indexed abstract does not identify the specific adverse effects responsible for SELECT’s discontinuations or provide a complete safety profile. That limits how specifically this report can characterize tolerability. The consultation-questions guide can help organize questions about adverse effects, follow-up, and treatment interruptions without treating trial averages as individualized advice.
FLOW and SUMMIT tested different clinical questions
FLOW studied 3,533 people with type 2 diabetes and chronic kidney disease, using weekly subcutaneous semaglutide at a study dose of 1.0 mg versus placebo. Its primary composite included kidney failure, a large sustained loss of kidney filtration, or kidney-related or cardiovascular death. Over median follow-up of 3.4 years, it reported 331 versus 410 first events and a hazard ratio of 0.76, with a 95% confidence interval of 0.66–0.88. Follow-up ended early after a prespecified interim analysis.
FLOW also reported fewer serious adverse events with semaglutide: 49.6% versus 53.8%. Its kidney population, endpoint, dose, and safety measure differ from SELECT’s. The FLOW analysis examines that distinct question. Novo Nordisk funded both studies, but shared sponsorship and the same drug do not make their estimates interchangeable.
SUMMIT instead tested tirzepatide, up to 15 mg injected weekly, in 731 people with obesity and heart failure with preserved ejection fraction. Over median follow-up of 104 weeks, cardiovascular death or worsening heart failure occurred in 9.9% versus 15.3%; the hazard ratio was 0.62, with a 95% confidence interval of 0.41–0.95. These trials are not a head-to-head ranking: they differ in drug, population, endpoint, and observation period.
| Trial and population | Studied intervention versus placebo | Primary event question |
|---|---|---|
| SELECT: established cardiovascular disease, BMI ≥27, no diabetes | Subcutaneous semaglutide 2.4 mg weekly | Cardiovascular death, nonfatal heart attack, or nonfatal stroke; HR 0.80 |
| FLOW: type 2 diabetes and chronic kidney disease | Subcutaneous semaglutide 1.0 mg weekly | Major kidney disease composite including cardiovascular death; HR 0.76 |
| SUMMIT: obesity and heart failure with ejection fraction ≥50% | Subcutaneous tirzepatide up to 15 mg weekly | Cardiovascular death or worsening heart failure; HR 0.62 |
SUMMIT shows why component results deserve attention
SUMMIT provides a concrete example of a composite improving without every component showing improvement. Worsening heart-failure events occurred in 8.0% with tirzepatide and 14.2% with placebo, with a hazard ratio of 0.54 and 95% confidence interval of 0.34–0.85. Cardiovascular deaths numbered eight versus five, with a hazard ratio of 1.58 and a much wider interval of 0.52–4.83.
Those small death counts and wide limits do not establish either a mortality benefit or a mortality harm. They do show why the favorable combined result cannot be relabeled a proven reduction in cardiovascular death. The SUMMIT analysis separates its event findings from its other primary endpoint, patient-reported health status.
At 52 weeks, SUMMIT’s between-group improvement in the Kansas City Cardiomyopathy Questionnaire clinical summary score was 6.9 points, with a 95% confidence interval of 3.3–10.6. Adverse events, mainly gastrointestinal, caused discontinuation in 6.3% versus 1.4%. Eli Lilly funded the trial. Neither its symptom result nor its component estimates can fill gaps in SELECT’s abstract.
Evidence for a product is not evidence for a program
On March 8, 2024, FDA announced a cardiovascular indication for Wegovy injection in adults with cardiovascular disease and overweight or obesity, alongside reduced-calorie diet and increased physical activity. That dated announcement supports the indication described; it is not current complete prescribing information. SELECT does not establish comparable cardiovascular outcomes for oral semaglutide, other formulations, or compounded preparations.
FDA states that compounded drugs are not approved or reviewed before marketing for safety, effectiveness, or quality. Its concerns include dosing errors and semaglutide salt ingredients; reports alone cannot establish event rates or causation. The medication-questions guide helps distinguish the identity of a product from the name used to advertise a service.
Editorial interpretation: clinical evidence and enrollment terms belong in separate columns of a decision. A comparison worksheet can keep them distinct. For documentary questions about payment or cancellation, readers can consult the CoreAge Rx review or Mochi Health review. These links do not establish that either provider offers the studied product, condition-specific care, or SELECT-like outcomes.
Questions & answers
Does SELECT prove that semaglutide prevents a first heart problem in someone without cardiovascular disease?
No. Participants already had cardiovascular disease. SELECT supports secondary prevention in its studied population, not a promise of primary prevention. Someone without established disease may have a different baseline risk, and SELECT’s 6.5% and 8.0% event proportions cannot simply be assigned to that person.
Is the benefit 20% or 1.5 percentage points?
Both describe the reported comparison, but on different scales. The 20% figure is a relative reduction in the hazard of a first primary event. The 1.5-percentage-point figure is the difference between the rounded observed event proportions, 8.0% and 6.5%. Neither should be substituted for the other.
Did SELECT show that weight loss caused the cardiovascular benefit?
The randomized comparison supports an effect of treatment assignment on the primary outcome. The indexed abstract does not establish how much benefit came through weight change versus other pathways. Separating those mechanisms requires additional analyses; an association between weight change and outcomes would not, by itself, settle causation.
Why not choose a treatment by comparing SELECT’s 20% with SUMMIT’s 38%?
The percentages concern different drugs, populations, and composite outcomes. SELECT tested semaglutide in established cardiovascular disease without diabetes; SUMMIT tested tirzepatide in obesity-related heart failure with preserved ejection fraction. Without a suitable direct comparison, the difference between their hazard reductions does not establish which treatment is better for the same person.
What uncertainty is worth discussing at a clinical visit?
Useful questions include how closely your medical history matches SELECT, what current prescribing information says, and how adverse effects and follow-up would be handled. It is also reasonable to ask which claims concern the combined endpoint rather than individual outcomes. Trial averages inform that discussion but do not determine a personal treatment choice.
Our assessment
SELECT provides substantial randomized evidence that weekly injected semaglutide reduced a three-component cardiovascular endpoint in adults with established cardiovascular disease, overweight or obesity, and no diabetes. Its practical meaning is clearest when the hazard ratio, absolute event proportions, observation period, and adverse-event discontinuations are read together. The result expands understanding beyond weight change, but it does not establish equal improvement in every component, primary-prevention benefit, or equivalence across products and care programs.
Sources & documentation
Scientific and official sources consulted October 20, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.
- Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. ↗
- FDA cardiovascular indication for Wegovy, March 8, 2024 ↗
- Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes. ↗
- Tirzepatide for Heart Failure with Preserved Ejection Fraction and Obesity. ↗
- FDA concerns about unapproved GLP-1 drugs ↗