A heart-failure trial can be positive without proving that treatment helps people live longer. SUMMIT illustrates why that distinction matters. Among 731 participants with obesity and heart failure with preserved ejection fraction, tirzepatide reduced a combined outcome of cardiovascular death or worsening heart failure compared with placebo. Participants also reported greater improvement in heart-failure health status. But the death counts alone did not establish a mortality benefit.
The useful reading is neither that the trial proved everything nor that uncertainty makes it uninformative. SUMMIT provides randomized evidence about a defined population, an injected treatment, and specific outcomes measured over time. This analysis uses the indexed primary report abstracts for SUMMIT and two comparison trials, together with available official FDA material on compounded drugs. It does not draw on an examination of the trials’ full protocols or supplements.
At a glance
- Who was studied
- SUMMIT randomized 731 people with heart failure, an ejection fraction of at least 50%, and a body-mass index of at least 30.Sources: [1]
- Treatment and observation
- Participants received once-weekly subcutaneous tirzepatide, up to 15 mg, or placebo. Median follow-up was 104 weeks.Sources: [1]
- Combined clinical outcome
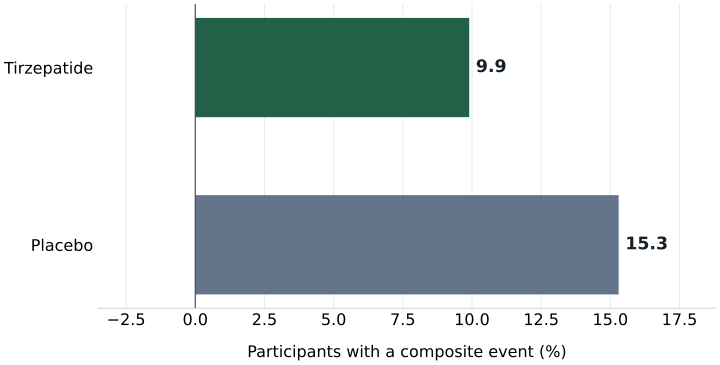
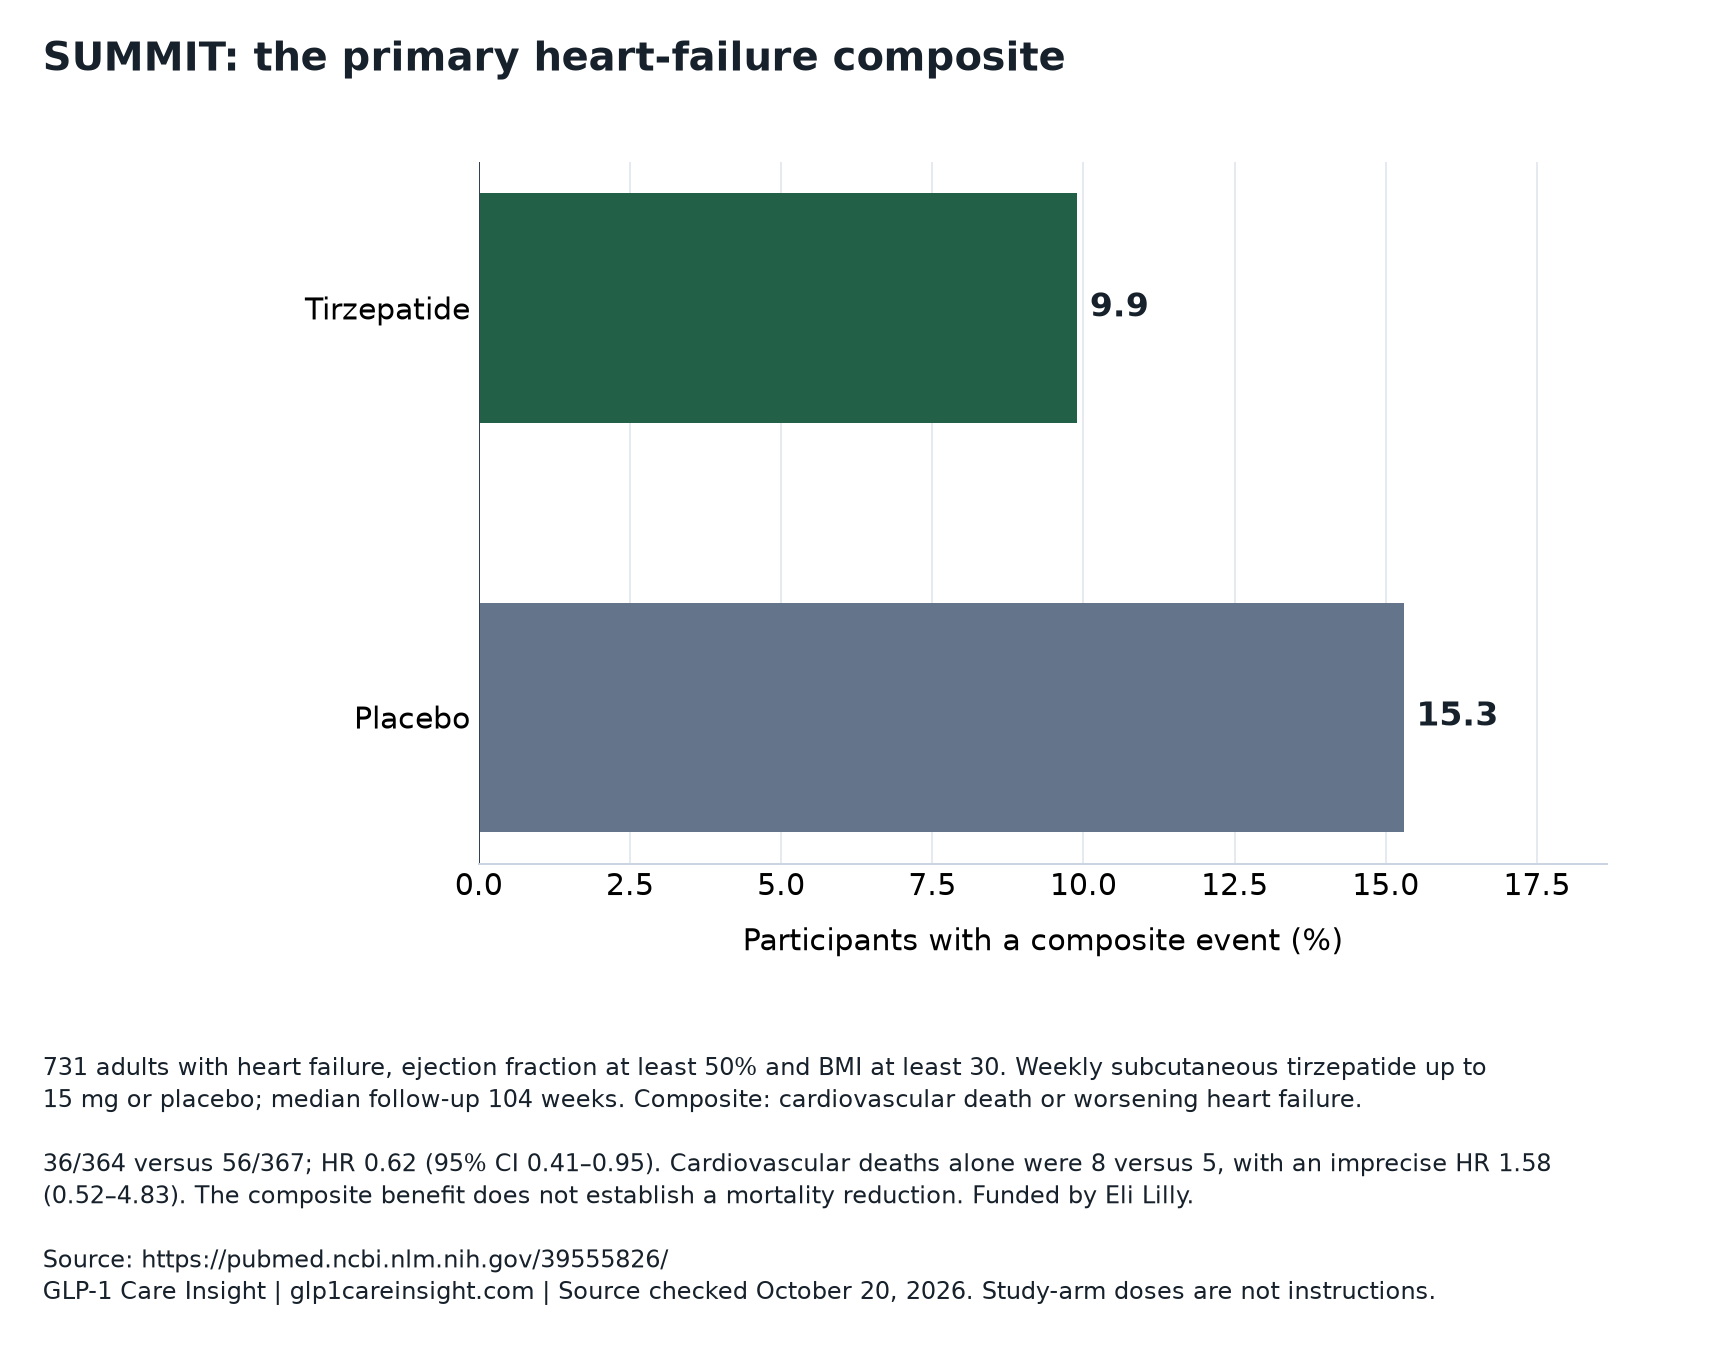
- Cardiovascular death or worsening heart failure occurred in 9.9% versus 15.3%; hazard ratio 0.62, 95% confidence interval 0.41–0.95.Sources: [1]
- Deaths require separate interpretation
- There were 8 cardiovascular deaths with tirzepatide and 5 with placebo; hazard ratio 1.58, 95% confidence interval 0.52–4.83. This did not establish an isolated mortality benefit.Sources: [1]
- Treatment discontinuation
- Adverse events, mainly gastrointestinal, led to trial-drug discontinuation in 6.3% of the tirzepatide group versus 1.4% of the placebo group.Sources: [1]
Preserved ejection fraction describes the population, not an absence of heart failure
SUMMIT required heart failure, an ejection fraction of at least 50%, and a body-mass index, or BMI, of at least 30. Ejection fraction describes the proportion of blood in the heart’s main pumping chamber that is expelled with each beat. A preserved percentage does not mean that someone cannot have heart failure. It identifies a different clinical category from heart failure with reduced ejection fraction.
BMI is weight in kilograms divided by height in meters squared. The BMI threshold means that SUMMIT directly tested a population with obesity, not everyone with preserved-ejection-fraction heart failure. Its findings should not automatically be extended to people below that threshold or to people whose ejection fraction is below 50%. Those are differences in the population being studied, not merely differences in terminology.
The indexed abstract does not supply the complete entry criteria, baseline disease severity, or detailed distribution of other illnesses and treatments. Consequently, the headline criteria are a starting point for judging relevance, not a complete patient-matching checklist. The central applicability question is how closely a person’s heart-failure phenotype and clinical circumstances resemble those of the trial participants.
Randomization tested weekly injected tirzepatide against placebo
SUMMIT was an international, double-blind, randomized, placebo-controlled trial. Investigators assigned 364 participants to tirzepatide and 367 to placebo in a 1:1 allocation. Randomization helps make the groups comparable, reducing the likelihood that differences in outcomes simply reflect who received treatment. Double blinding limits the influence of knowing the assignment on behavior and outcome reporting.
The studied intervention was tirzepatide given subcutaneously—under the skin—once weekly, at doses up to 15 mg. These details identify the study arm; they are not dosing instructions. The comparator was placebo, not semaglutide or another active weight-management treatment. SUMMIT therefore cannot establish that tirzepatide is superior to those alternatives for heart failure.
Treatment was assigned for at least 52 weeks, and median follow-up was 104 weeks, approximately two years. Median follow-up describes the midpoint of observation durations, not an identical two-year visit for every participant. Eli Lilly funded the trial. Sponsorship is relevant context, while the randomized design, stated outcomes, estimates, and uncertainty remain the main basis for evaluating its findings.
STUDY DATA · GLP-1 Care Insight
SUMMIT: the primary heart-failure composite
731 adults with heart failure, ejection fraction at least 50% and BMI at least 30. Weekly subcutaneous tirzepatide up to 15 mg or placebo; median follow-up 104 weeks. Composite: cardiovascular death or worsening heart failure.
| Study group | Participants with a composite event (%) |
|---|---|
| Tirzepatide | 9.9 |
| Placebo | 15.3 |
36/364 versus 56/367; HR 0.62 (95% CI 0.41–0.95). Cardiovascular deaths alone were 8 versus 5, with an imprecise HR 1.58 (0.52–4.83). The composite benefit does not establish a mortality reduction. Funded by Eli Lilly.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
The main event result combines two different outcomes
One primary endpoint was a composite: adjudicated cardiovascular death or a worsening-heart-failure event. A composite groups multiple outcomes into one analysis. Adjudication means events were assessed against study criteria, although the abstract does not provide the complete adjudication procedures. The analysis measured time to the first qualifying event rather than simply counting every event a participant experienced.
The composite occurred in 36 of 364 tirzepatide participants, or 9.9%, and 56 of 367 placebo participants, or 15.3%. Subtracting the reported percentages gives an observed difference of 5.4 percentage points. That is an absolute difference between the reported event proportions over the trial’s follow-up, not a 5.4% relative reduction and not a fixed annual event-rate difference.
The hazard ratio was 0.62, with a 95% confidence interval of 0.41–0.95. It summarizes the relative event hazard over time, incorporating when events occurred. Describing it as an estimated 38% lower hazard is appropriate. Calling it a 38-percentage-point reduction, or treating it as the same calculation as the difference between the two percentages, would not be.
| Outcome | Tirzepatide versus placebo | Hazard ratio (95% CI) |
|---|---|---|
| Cardiovascular death or worsening heart failure | 36/364 (9.9%) versus 56/367 (15.3%) | 0.62 (0.41–0.95) |
| Worsening heart-failure event | 29/364 (8.0%) versus 52/367 (14.2%) | 0.54 (0.34–0.85) |
| Cardiovascular death | 8/364 (2.2%) versus 5/367 (1.4%) | 1.58 (0.52–4.83) |
Worsening heart failure and cardiovascular death tell different stories
Worsening-heart-failure events occurred in 29 tirzepatide participants, compared with 52 placebo participants: 8.0% versus 14.2%. The hazard ratio was 0.54, with a 95% confidence interval of 0.34–0.85. This component supports the interpretation that fewer worsening-heart-failure events were central to the favorable composite result. The abstract does not provide the complete event definition, so these counts should not simply be relabeled as hospitalizations.
Cardiovascular deaths numbered 8 with tirzepatide and 5 with placebo, corresponding to 2.2% and 1.4%. The hazard ratio was 1.58, with a wide 95% confidence interval of 0.52–4.83. The point estimate was above 1, but the interval included both lower and substantially higher hazards. These sparse data establish neither a cardiovascular mortality benefit nor a definitive increase in cardiovascular mortality.
The components also cannot simply be added. In the tirzepatide group, 29 participants with worsening events plus 8 cardiovascular deaths would total 37, yet only 36 participants met the composite. Component categories can overlap because a participant may worsen and later die. A time-to-first-event composite counts that person once for its primary analysis, not once for each component.
Confidence intervals explain why the mortality answer remains open
A confidence interval describes the uncertainty around an estimate under the analysis’s assumptions. For the composite, the interval of 0.41–0.95 stayed below the no-difference value of 1. It supports a lower composite hazard, while leaving uncertainty about the magnitude: the evidence is compatible with effects ranging from comparatively modest to substantially larger.
The cardiovascular-death interval is much wider because the estimate rests on only 13 deaths across both groups. A trial can provide useful information about a more frequent composite while remaining imprecise about a rarer component. The positive composite result does not make the death estimate precise, and the uncertain death result does not erase the evidence about worsening heart failure.
A productive consultation question is therefore not just whether the trial was positive, but which outcome a proposed benefit concerns. Fewer worsening events, better reported health status, and longer survival are distinct claims requiring distinct evidence. The evidence-questions guide offers a framework for keeping a numerical claim attached to its actual endpoint rather than a broader promise.
The symptom score adds information that event counts cannot
SUMMIT’s other primary endpoint was change from baseline to week 52 in the Kansas City Cardiomyopathy Questionnaire clinical summary score, or KCCQ-CSS. Scores range from 0 to 100, with higher scores indicating better heart-failure health status. This patient-reported measure captures an aspect of illness that a death-or-worsening-event endpoint cannot fully describe.
Mean improvement was 19.5 points with tirzepatide and 12.7 points with placebo. The reported between-group difference was 6.9 points, with a 95% confidence interval of 3.3–10.6. That reported estimate should be retained rather than replaced by subtraction of the rounded group values. The abstract does not give enough analysis detail to reconstruct the difference precisely.
Both groups improved, so the entire 19.5-point change cannot be attributed to tirzepatide. The randomized comparison estimates the additional improvement associated with assignment to treatment. Likewise, a mean difference does not reveal how many individuals experienced a particular degree of benefit. It supports an average improvement in health status, not a guarantee of an identical change for every participant.
Discontinuations show a meaningful tolerability trade-off
Adverse events leading to trial-drug discontinuation occurred in 23 tirzepatide participants and 5 placebo participants: 6.3% versus 1.4%. The events were mainly gastrointestinal. The observed difference was 4.9 percentage points. This is a concrete tolerability finding, not a basis for describing the treatment as uniformly safe or uniformly difficult to tolerate.
Discontinuation is only one safety measure. It does not capture every adverse event, its duration, or its severity. The indexed abstract does not provide a comprehensive safety table or detailed breakdown of gastrointestinal symptoms. It also does not establish how adverse-event patterns would look in every clinical population or with substantially longer exposure.
Benefit and tolerability should therefore remain visible together: fewer participants experienced the primary composite, while more stopped the trial drug because of adverse events. Those figures describe different outcomes and cannot be reduced to a single simple balance. The consultation-questions guide can help organize questions about expected benefits, adverse effects, monitoring, and who handles concerns during ongoing care.
STEP-HFpEF tested a different treatment and a different main question
STEP-HFpEF randomized 529 people with preserved-ejection-fraction heart failure and BMI of at least 30 to once-weekly semaglutide 2.4 mg or placebo for 52 weeks. Its dual primary endpoints were KCCQ-CSS change and body-weight change—not SUMMIT’s cardiovascular-death or worsening-heart-failure composite. Novo Nordisk funded the trial. Its design emphasized symptoms and weight over one year.
The reported KCCQ-CSS difference favored semaglutide by 7.8 points, with a 95% confidence interval of 4.8–10.9. Weight changed by −13.3% versus −2.6%, an estimated difference of −10.7 percentage points. Six-minute walk distance improved by an estimated additional 20.3 meters, with a confidence interval of 8.6–32.1 meters. Serious adverse events occurred in 13.3% versus 26.7%.
Those results complement SUMMIT but do not rank the drugs. Different participants, follow-up, endpoints, and analyses prevent a fair indirect comparison of efficacy or safety. STEP-HFpEF also used a hierarchical composite with a win ratio, which is not interchangeable with SUMMIT’s time-to-first-event hazard ratio. The STEP-HFpEF analysis explains why symptoms, walking performance, and event outcomes answer related but separate questions.
SELECT’s cardiovascular result is not SUMMIT’s heart-failure result
SELECT enrolled 17,604 adults aged at least 45 with established cardiovascular disease, BMI of at least 27, and no history of diabetes. It compared weekly subcutaneous semaglutide 2.4 mg with placebo. Its primary endpoint combined cardiovascular death, nonfatal myocardial infarction, and nonfatal stroke. Unlike SUMMIT, entry was not defined by obesity plus preserved-ejection-fraction heart failure.
Over mean follow-up of 39.8 months, the SELECT composite occurred in 6.5% versus 8.0%; the hazard ratio was 0.80, with a 95% confidence interval of 0.72–0.90. Adverse events led to permanent trial-product discontinuation in 16.6% versus 8.2%. Novo Nordisk funded SELECT. Its larger sample does not make its endpoint interchangeable with SUMMIT’s; it answers a different cardiovascular question.
Comparing 0.62 in SUMMIT with 0.80 in SELECT cannot establish which drug is better. Baseline risk, qualifying conditions, event definitions, and observation periods differ. The SELECT analysis provides context for its arterial-event composite. Together, the trials illustrate why the broad phrase cardiovascular benefit needs an accompanying description of the population and the actual outcomes measured.
| Trial | Population and comparison | Primary outcome focus |
|---|---|---|
| SUMMIT | 731 people with heart failure, EF ≥50%, BMI ≥30; weekly injected tirzepatide versus placebo | Cardiovascular death or worsening heart failure; KCCQ-CSS change |
| STEP-HFpEF | 529 people with HFpEF and BMI ≥30; weekly semaglutide versus placebo | KCCQ-CSS change and body-weight change at 52 weeks |
| SELECT | 17,604 people with established cardiovascular disease, BMI ≥27, no diabetes; weekly injected semaglutide versus placebo | Cardiovascular death, nonfatal myocardial infarction, or nonfatal stroke |
A trial result does not validate a product offer or care contract
SUMMIT does not establish equivalent outcomes for compounded tirzepatide, oral routes, or other formulations. FDA states that compounded drugs are not FDA approved and are not reviewed before marketing for safety, effectiveness, or quality. It recommends compounded products only when a patient’s needs cannot be met by an FDA-approved drug. The agency also identifies dosing errors and concerns about semaglutide salt ingredients; reports alone cannot establish event rates or causation.
Editorial interpretation: the practical task is to separate evidence about a studied medicine from documentary questions about the product and service being offered. Medication identity, formulation, pharmacy information, and follow-up arrangements matter, but a provider’s terms cannot establish trial-level effectiveness. The medication-questions guide helps distinguish those product questions from broader marketing claims.
For contract review, the CoreAge Rx review and Mochi Health review can be used to identify documentary terms to check before payment. These links do not imply either provider offers the SUMMIT intervention, heart-failure-specific care, or the outcomes observed in the trial. Neither SUMMIT nor the comparison reports constitute current prescribing information.
Questions & answers
Did SUMMIT prove that tirzepatide prevents cardiovascular death?
No. The combined endpoint favored tirzepatide, but cardiovascular deaths were 8 versus 5, with a hazard ratio of 1.58 and a wide 95% confidence interval of 0.52–4.83. The mortality component was too imprecise to establish either a survival benefit or a definitive increase in cardiovascular mortality. The stronger component evidence concerned worsening heart failure.
Why do the individual event counts exceed the composite count?
The component groups can overlap. A participant can experience worsening heart failure and later die from a cardiovascular cause. Adding the component counts would count that person twice, while the primary time-to-first-event analysis counts the first qualifying event. The composite therefore describes participants reaching an endpoint, not the sum of every component occurrence.
Does the health-status result mean everyone felt better?
No. The reported 6.9-point KCCQ-CSS advantage is a between-group average, with a 95% confidence interval of 3.3–10.6. It does not show the distribution of individual experiences. Some participants could have improved more, less, or not at all. The abstract does not provide the responder information needed to quantify those possibilities.
Can SUMMIT and STEP-HFpEF identify the better medicine?
Not directly. They studied different medicines in separate placebo-controlled trials, with different primary endpoints and follow-up structures. Similar-looking symptom-score differences do not create a head-to-head comparison. SUMMIT supplies evidence about its event composite and health status; STEP-HFpEF supplies evidence centered on symptoms, weight, and physical function.
Does this evidence explain exactly how tirzepatide improved outcomes?
No. Randomization supports a treatment-effect interpretation for the measured outcomes, but it does not by itself identify the pathway responsible. The indexed SUMMIT abstract does not separate contributions from weight change, metabolic effects, or other possible mechanisms. Establishing that an intervention helped and explaining precisely why it helped are different scientific tasks.
Our assessment
SUMMIT provides meaningful randomized evidence that weekly injected tirzepatide reduced a cardiovascular-death or worsening-heart-failure composite and improved reported health status in people with obesity and preserved-ejection-fraction heart failure. The component results support fewer worsening-heart-failure events, not an isolated mortality claim. Increased adverse-event discontinuation is part of the same evidence. The most faithful interpretation preserves all three findings rather than replacing them with a broad promise about heart health.
Sources & documentation
Scientific and official sources consulted October 20, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.