What happens after substantial weight loss with tirzepatide: does the lower weight persist, does treatment need to continue, or could a lower dose maintain some of the benefit? SURMOUNT-4 addressed the first two questions by randomly assigning people who had already completed 36 weeks of treatment either to continue tirzepatide or to switch to placebo. Continued treatment produced additional average loss; withdrawal produced substantial average regain. That finding is important, but it is not a prediction that every person will follow the same trajectory.
Understanding the study requires keeping two starting points separate: weight before any study treatment and weight when the randomized withdrawal phase began. It also requires distinguishing SURMOUNT-4 from the newer 2026 SURMOUNT-MAINTAIN report, which directly tested a lower-dose maintenance arm. This analysis uses the indexed primary-report abstracts for those two trials, the available full STEP 1 extension article, and official NIDDK and FDA material—not a review of every trial protocol or supplement.
At a glance
- Enrollment versus randomization
- SURMOUNT-4 enrolled 783 people in its treatment lead-in; 670 were randomized at week 36, with 335 assigned to each group.Sources: [1]
- Initial weight reduction
- Participants completing the 36-week lead-in had lost an average of 20.9% of their starting weight.Sources: [1]
- Randomized maintenance result
- From week 36 to week 88, mean weight changed by −5.5% with continued tirzepatide versus +14.0% after switching to placebo.Sources: [1]
- Retention of initial loss
- At week 88, 89.5% of continued-treatment participants maintained at least 80% of their lead-in weight loss, compared with 16.6% receiving placebo.Sources: [1]
- Newer maintenance-dose evidence
- SURMOUNT-MAINTAIN tested continued maximum tolerated tirzepatide, reduction to 5 mg, and placebo after a 60-week weight-loss period; average baseline-to-week-112 losses were 21.9%, 16.6%, and 9.9%, respectively.Sources: [2]
A withdrawal trial asks what continued treatment adds
SURMOUNT-4 was a phase 3 study conducted at 70 sites in four countries. Eligible adults had a body mass index, or BMI, of at least 30, or at least 27 with a weight-related complication. Diabetes was excluded. Among the 670 randomized participants, mean age was 48 years, 71% were women, and reported mean weight was 107.3 kilograms.
Everyone initially received tirzepatide during a 36-week open-label period, meaning treatment identity was known. The study used once-weekly injections under the skin, with maximum tolerated doses of 10 or 15 mg. These doses identify the studied treatment strategy; they are not instructions for selecting an individual dose.
Only afterward did the double-blind comparison begin: participants continued tirzepatide or switched to placebo for another 52 weeks, with diet and physical activity included in the treatment context. Randomization makes this a stronger test of continuation versus withdrawal than simply comparing people who independently decide to stop or continue, whose circumstances may differ substantially.
Why 783 starters are not 670 randomized participants
The 783 people entering the lead-in were not all included in the randomized comparison. By week 36, 670 proceeded to randomization: 113 fewer than entered, or approximately 14.4% of the initial group. The indexed abstract does not give the detailed reasons for every departure, so that difference cannot be labeled entirely as adverse-effect discontinuation or treatment failure.
This design creates a selected population: people who completed a lengthy treatment period and reached the studied maximum tolerated dose strategy. It is especially relevant to maintenance after established treatment, but less directly representative of everyone receiving a first prescription, including those who cannot tolerate treatment or leave care early.
The average 20.9% lead-in loss likewise describes the participants who completed that phase, not a guaranteed result among all 783 entrants. Selection does not invalidate the subsequent randomized comparison. It changes the question the comparison can answer: what happened among people able to reach this maintenance decision point, rather than what happens to every person who starts.
STUDY DATA · GLP-1 Care Insight
SURMOUNT-4: change after randomization
670 adults randomized after a 36-week tirzepatide lead-in; adults had obesity or overweight with a complication, without diabetes. The chart covers weeks 36–88, using weight at week 36 as the reference.
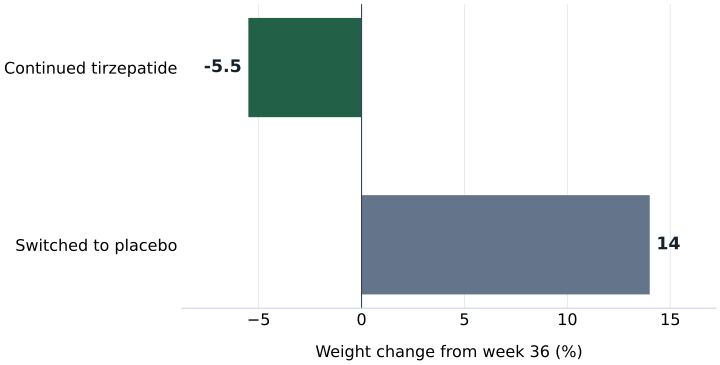
| Study group | Weight change from week 36 (%) |
|---|---|
| Continued tirzepatide | -5.5 |
| Switched to placebo | 14 |
Negative means further loss; positive means regain. The 20.9% lead-in loss uses a different baseline and cannot be added directly to these percentages. This selected population completed the lead-in. Trial sponsor: Eli Lilly.
Original visualization of published aggregate data. No individual prediction or provider performance is represented. Original research ↗
Two baselines explain the apparently conflicting percentages
The primary endpoint—the main measurement specified for the trial—was mean percentage weight change from week 36 to week 88. Week 36 was the randomization baseline, after the initial loss. The −5.5% result with continued treatment and +14.0% result with placebo therefore use the lower, post-loss weight as their denominator.
A worked illustration helps. If starting weight is represented by 100 units, a 20.9% reduction leaves 79.1 units. Adding 14% of 79.1 brings weight to about 90.2 units, still roughly 9.8% below the original 100. Losing another 5.5% of 79.1 leaves about 74.7 units. This illustrates the arithmetic, not an individual forecast or an exact reconstruction of the trial analysis.
The report’s actual overall mean reductions from week 0 to week 88 were 25.3% with continued tirzepatide and 9.9% with placebo. Small differences from simplified calculations reflect rounding and the fact that group-average percentages need not combine exactly like one person's measurements. The evidence-question guide offers a useful habit: identify the starting denominator before comparing headline percentages.
| Measurement | Reported result | Meaning |
|---|---|---|
| Week 0 to week 36 | 20.9% mean reduction | Initial loss among lead-in completers |
| Week 36 to week 88 | −5.5% continued treatment; +14.0% placebo | Change relative to weight at randomization |
| Week 0 to week 88 | 25.3% versus 9.9% mean reduction | Net change relative to original starting weight |
| Retention at week 88 | 89.5% versus 16.6% | Participants maintaining at least 80% of lead-in loss |
The treatment difference is not a risk reduction
The reported between-group difference in the primary endpoint was −19.4 percentage points, with a 95% confidence interval from −21.2 to −17.7. It is a difference between mean percentage weight changes, not a 19.4% reduction in the risk of regaining weight. The displayed rounded arm estimates subtract to 19.5 points; the reported analysis gives 19.4.
The confidence interval describes statistical uncertainty around the estimated average treatment contrast. Its range strongly favors continuation under the trial conditions. It does not describe the range of individual outcomes, and it cannot establish that a particular person will lose another 5.5% or regain exactly 14%.
A separate outcome translates maintenance into a threshold: retaining at least 80% of the loss achieved during lead-in. For illustration, someone who lost 20 weight units would meet that threshold by retaining at least 16 units of loss. The 89.5% versus 16.6% finding shows a large separation, while also demonstrating that neither arm had a uniform outcome. Maintaining a threshold is different from maintaining precisely the same weight.
SURMOUNT-MAINTAIN directly studied a lower-dose option
It would now be inaccurate to say maintenance-dose research does not exist. The 2026 SURMOUNT-MAINTAIN report describes a phase 3b trial at 20 US sites, lasting 112 weeks. After 60 weeks of open-label, once-weekly subcutaneous tirzepatide at a maximum tolerated 10 or 15 mg, participants were assigned to continue that strategy, reduce to 5 mg, or switch to placebo for 52 weeks.
Adults qualified with BMI at least 30, or at least 27 with a weight-related comorbidity, and a history of an unsuccessful dietary weight-loss effort. Of 441 enrolled participants receiving treatment during the weight-loss period, 378 were randomized: 140 to maximum tolerated treatment, 144 to 5 mg, and 94 to placebo. Overall, 345 randomized participants, or 91%, completed the study.
Unlike SURMOUNT-4's primary endpoint beginning at randomization, MAINTAIN's primary endpoint measured percentage change from the original baseline to week 112. Its estimates therefore describe the combined weight-loss and maintenance periods. The study supplies evidence about one defined dose-reduction strategy, not proof that any lower dose, intermittent schedule, or taper would have equivalent effects.
| Randomized arm | Mean weight change, 95% CI | Difference versus placebo, 95% CI |
|---|---|---|
| Maximum tolerated tirzepatide, 10 or 15 mg | −21.9% (−23.5 to −20.3) | −12.0 percentage points (−13.8 to −10.1) |
| Tirzepatide reduced to 5 mg | −16.6% (−18.0 to −15.1) | −6.6 percentage points (−8.3 to −5.0) |
| Placebo | −9.9% (−11.1 to −8.8) | Reference group |
Rescue treatment changes how MAINTAIN should be read
Beginning at week 84, 24 weeks after randomization, MAINTAIN allowed rescue tirzepatide when regain exceeded 50% of previously lost weight. This was not a trial in which every participant remained indefinitely on the original assignment regardless of regain. The rescue rule matters both clinically and statistically.
Reported rescue use was 11 of 138 participants, or 8%, in the maximum tolerated arm; 35 of 142, or 25%, in the 5-mg arm; and 60 of 90, or 67%, in the placebo arm. These denominators differ from the original randomized counts. The pattern supports better maintenance with ongoing treatment while showing that substantial regain still occurred for some participants receiving active medication.
The primary analysis used a modified treatment-regimen estimand: a defined way of answering the treatment question despite events such as discontinuation or rescue. It included all randomized participants and assumed those starting rescue would obtain no further benefit from their assigned study treatment. Consequently, the reported estimates are not simply observed final weights after everyone received whatever rescue treatment they needed.
STEP 1 supports concern about regain—but is a different experiment
The STEP 1 extension followed withdrawal of semaglutide, not tirzepatide. The original trial randomized 1,961 adults without diabetes to once-weekly subcutaneous semaglutide 2.4 mg or placebo with lifestyle intervention for 68 weeks. The exploratory extension analyzed 327 participants from selected sites after treatment ended, rather than randomly assigning a fresh continuation-versus-withdrawal comparison.
Both medication and structured lifestyle intervention stopped at week 68. In the extension sample, mean loss with semaglutide had been 17.3%; participants regained 11.6 percentage points relative to original baseline over the following year, leaving a reported net loss of 5.6% at week 120. The common description of regaining about two-thirds refers to the fraction of prior loss regained—not two-thirds of total body weight.
Different drugs, initial treatment durations, selected samples, and lifestyle-support arrangements prevent a clean numerical ranking against SURMOUNT-4. The STEP 1 extension analysis examines that distinction further. Likewise, a direct-comparison study addresses a different question from withdrawal: relative treatment effects cannot be inferred simply by placing separate maintenance trials side by side.
Weight maintenance and health maintenance are related, not identical
The STEP 1 extension measured blood pressure, glucose regulation, lipids, and inflammation alongside weight. Most cardiometabolic improvements moved back toward baseline after withdrawal. For example, observed mean systolic blood pressure in the semaglutide arm was 129 mmHg initially, 121 at week 68, and 131 at week 120.
Other measures retained some improvement. Mean HbA1c, a marker of average blood glucose, changed from 5.7% initially to 5.2% during treatment and 5.6% after the off-treatment year. These observed group means involved different numbers of available measurements over time. They do not demonstrate a uniform reversal or preservation of every health effect.
These are risk-factor measurements, not proof of changes in heart attacks, kidney failure, or mortality after withdrawal. Nor does their movement establish exactly how much was caused by weight regain versus loss of medication effects or other changes. Longer follow-up is needed to determine whether remaining weight and metabolic benefits persist, diminish further, or stabilize.
Tolerability findings do not disappear during maintenance
In SURMOUNT-4, the most common adverse events were gastrointestinal, mostly mild to moderate, and more common with tirzepatide than placebo. The indexed abstract does not supply detailed event rates or a complete serious-adverse-event breakdown. It therefore supports that specific tolerability description, not a blanket claim that long-term treatment was safe for everyone.
MAINTAIN likewise reported gastrointestinal events as the most common adverse events with tirzepatide, usually mild to moderate and occurring mostly during dose escalation. Because both trials randomized people after prolonged active treatment, their maintenance populations should not be treated as an unselected picture of tolerability among new starters. The STEP 1 extension did not systematically collect adverse events during off-treatment follow-up.
Evidence transparency also includes funding. MAINTAIN reports Eli Lilly funding; STEP 1 was funded by Novo Nordisk, with company employees among the extension authors. The SURMOUNT-4 indexed abstract used here does not state funding. Sponsorship is relevant context for appraisal, but it neither replaces evaluation of randomization and endpoints nor automatically negates the findings.
Translate the evidence into questions, not a treatment script
NIDDK describes duration of weight-management medication use as depending on benefit and tolerability, with health history, other medicines, adverse effects, and cost considered with a healthcare professional. A useful discussion separates observed benefit, treatment burden, and uncertainty about alternatives. The consultation-question guide can help organize those topics without turning trial averages into a personal treatment plan.
Editorial interpretation: evidence favoring ongoing treatment makes continuity and affordability relevant planning questions, but it does not establish a subscription length or an insurance entitlement. The coverage-question guide separates plan terms from clinical results. A documentary review such as the CoreAge Rx review can be used to check written payment and cancellation terms—not to infer access to the studied product or equivalent outcomes.
Finally, these clinical results do not transfer automatically to a provider, compounded preparation, oral route, or other formulation. FDA states that compounded drugs are not approved or reviewed before marketing for safety, effectiveness, or quality, and identifies concerns including dosing errors and semaglutide salt ingredients. The medication-identity guide helps distinguish a product claim from evidence about the actual studied treatment.
Questions & answers
Does SURMOUNT-4 mean everyone regains all their weight after stopping?
No. The placebo group regained substantial weight on average but remained 9.9% below original baseline at week 88. Some participants retained at least 80% of their initial loss. The result establishes a strong average advantage for continuation over 52 weeks, not an inevitable individual outcome or a lifetime trajectory.
Why can 14% regain still leave someone below starting weight?
The 14% was calculated from the lower weight at week 36, not original starting weight. Percentages with different denominators cannot simply be subtracted. A smaller post-loss body weight is the base for the regain calculation, which is why substantial regain and a remaining net loss can coexist.
Is reducing the dose now supported by research?
A specific reduction strategy has been studied. SURMOUNT-MAINTAIN tested 5 mg after 60 weeks on maximum tolerated 10 or 15 mg treatment. Average results were better than placebo but less favorable numerically than continued maximum tolerated treatment, and rescue treatment was more frequent. This is evidence for discussion, not an individualized dosing recommendation.
Do these trials show that tapering prevents regain?
No. SURMOUNT-4 compared continuation with switching to placebo. MAINTAIN tested a defined lower-dose arm, not a general taper-to-discontinuation strategy. Neither indexed report establishes that progressively reducing doses, spacing injections, or eventually stopping will preserve the same weight loss.
What remains most uncertain for someone considering long-term treatment?
Important unknowns include individual response to a lower dose, outcomes beyond the observed maintenance year, and how trial results translate to people who could not complete initial treatment. Benefit, adverse effects, and access also need separate consideration. Neither a study average nor a coverage policy resolves those questions for one person.
Our assessment
SURMOUNT-4 provides strong randomized evidence that, among adults without diabetes who completed its tirzepatide lead-in, continued treatment maintained and augmented weight reduction more effectively than withdrawal over the next year. SURMOUNT-MAINTAIN adds meaningful evidence that a studied lower-dose strategy can outperform discontinuation, while not matching the numerical maintenance results of continued maximum tolerated treatment. Together, the trials support treating maintenance as an active phase of care rather than assuming initial loss will persist unchanged. They do not identify a universal dose, establish lifelong outcomes, or justify transferring results to unstudied products and care arrangements.
Sources & documentation
Scientific and official sources consulted October 20, 2026. Study findings apply to the populations, products and time periods described; they are not provider outcome data.
- Continued Treatment With Tirzepatide for Maintenance of Weight Reduction in Adults With Obesity: The SURMOUNT-4 Randomized Clinical Trial. ↗
- Tirzepatide for maintenance of bodyweight reduction in people with obesity in the USA (SURMOUNT-MAINTAIN): a multicentre, double-blind, randomised, placebo-controlled trial. ↗
- Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. ↗
- NIDDK prescription medications for overweight and obesity ↗
- FDA concerns about unapproved GLP-1 drugs ↗